
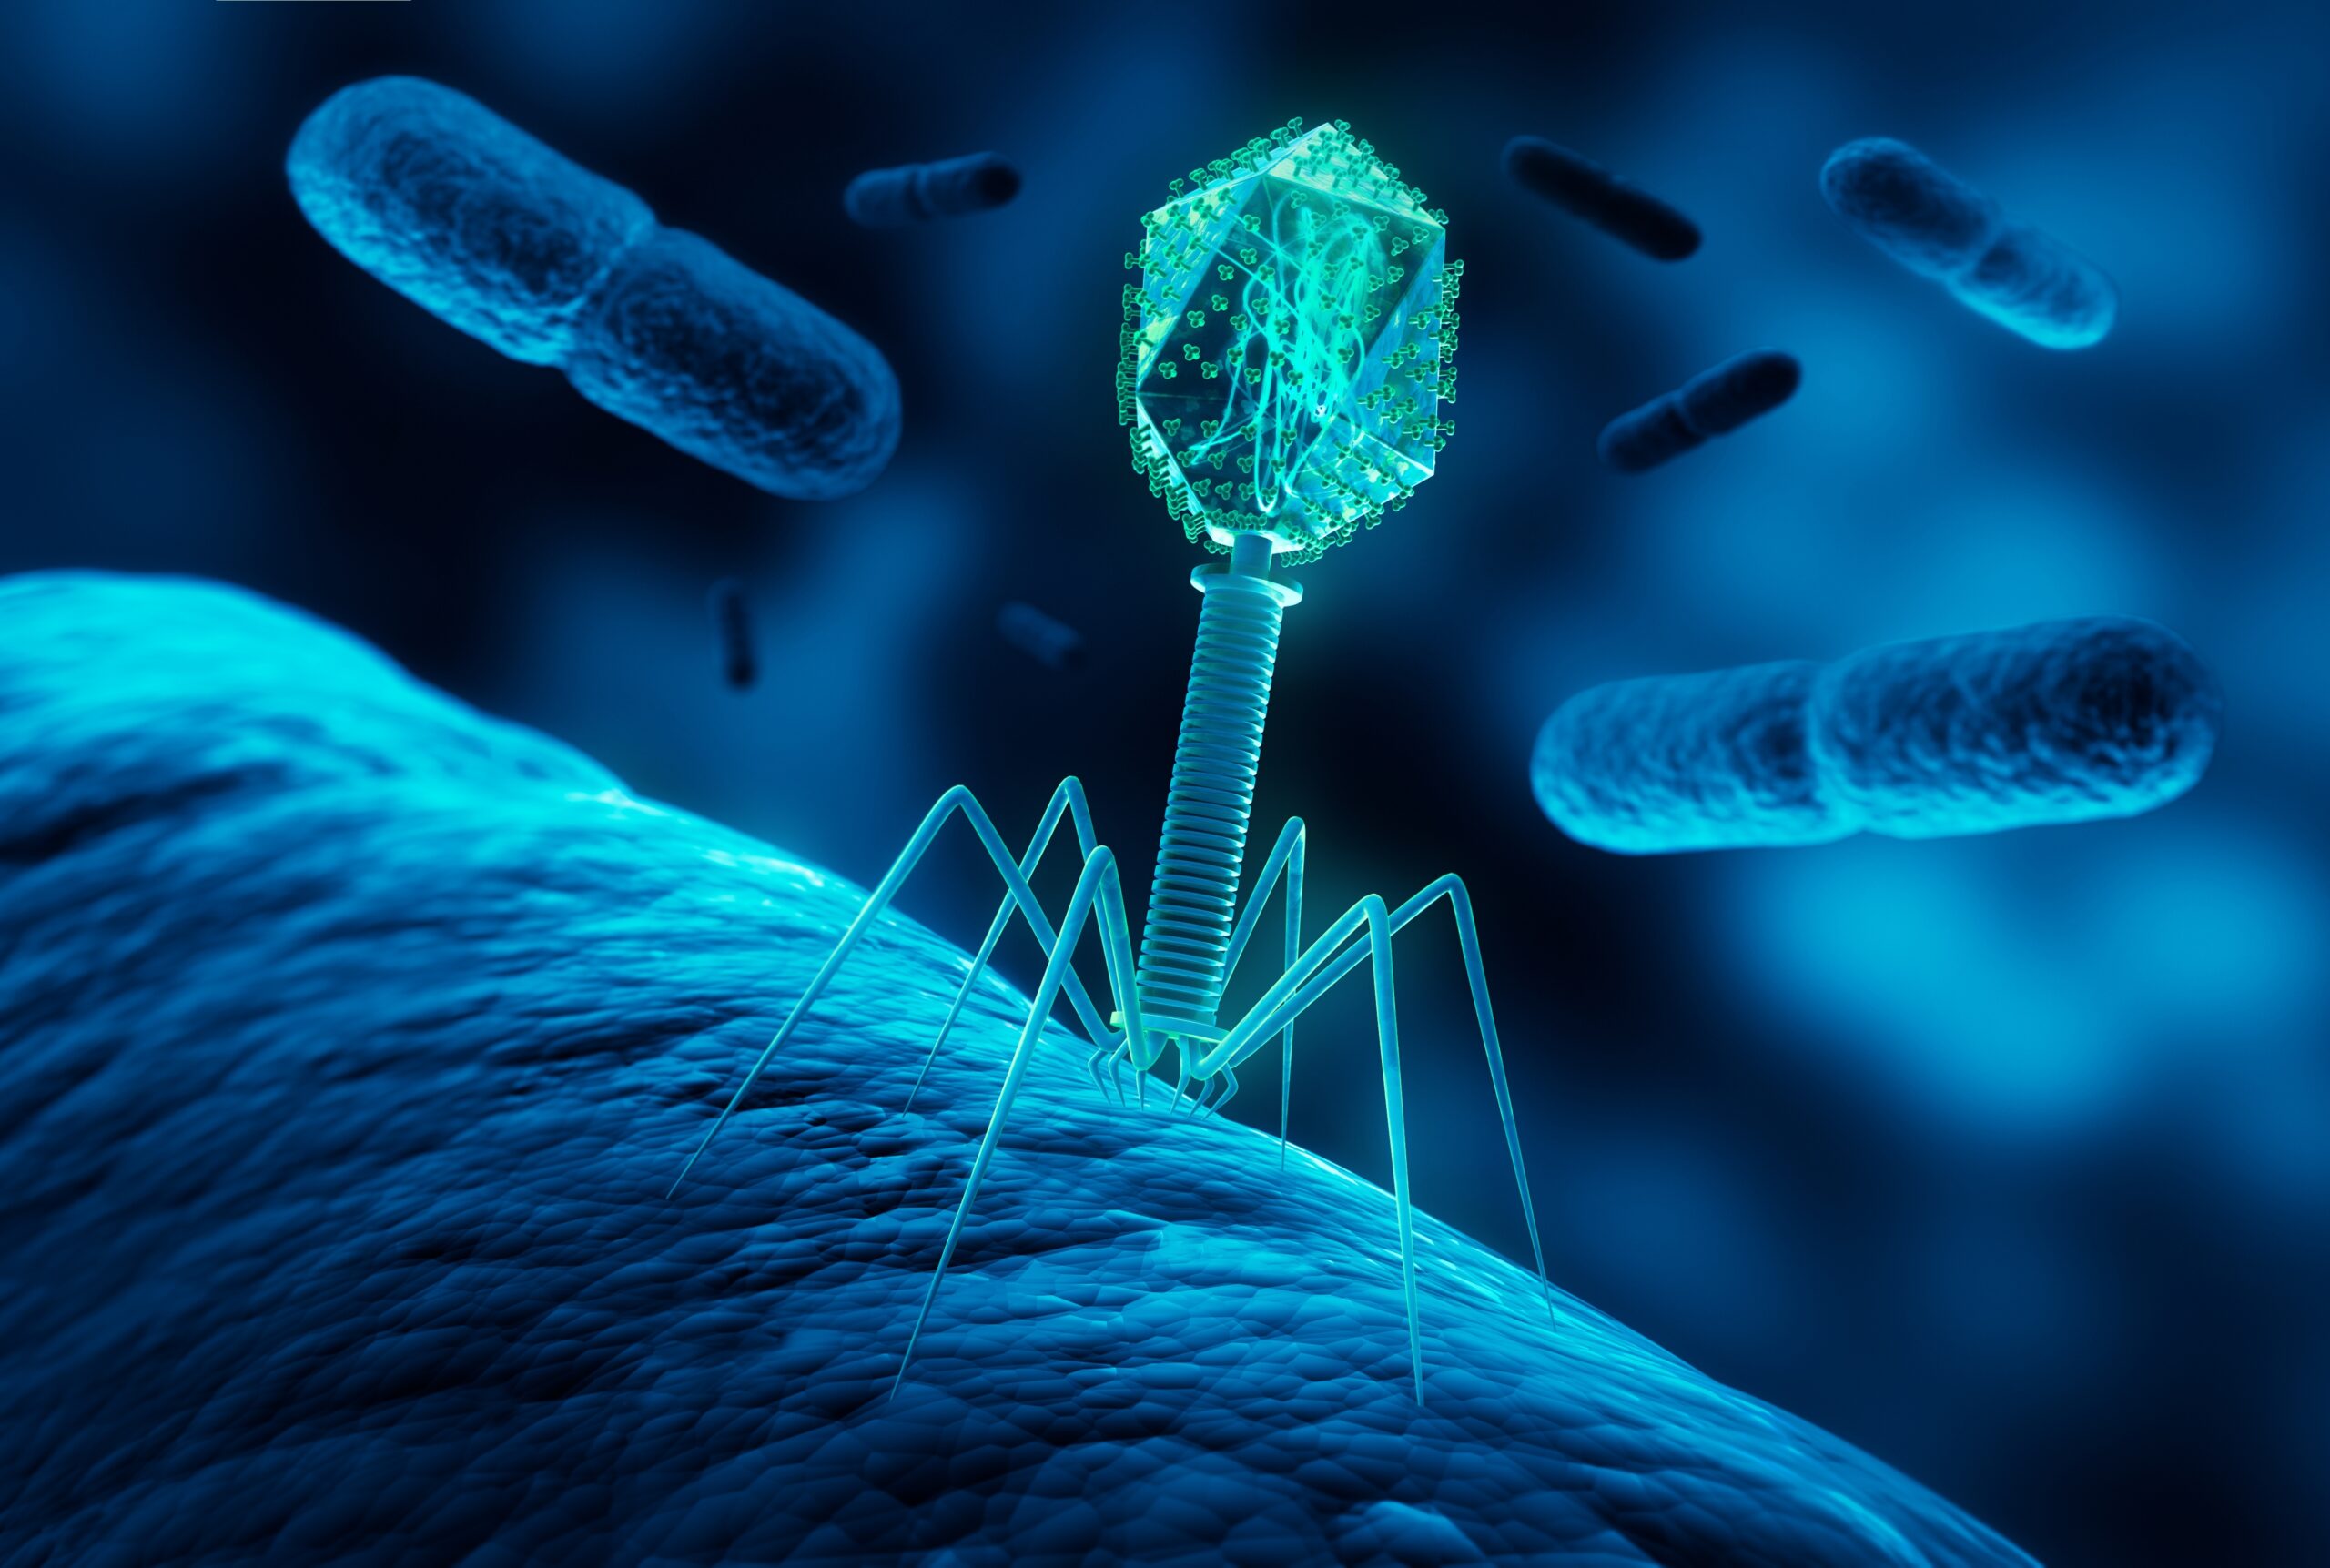
A new development is emerging on the landscape of the fight against antibiotic resistance, a phenomenon that in the last two decades has made the classic therapeutic arsenal for treating infections based on antibiotics increasingly limited. Phage therapy, born in the 1920s, is reappearing in the headlines as a possible therapeutic alternative, for now still experimental.
Phage therapy is based on the use of bacteriophages (“phages”) to kill the bacteria responsible for infections. These are viruses widely dispersed in the environment, for example also present as components of the human gut microbiota, where they help regulate the amounts of bacteria present. Phages exhibit an extremely high specificity toward particular bacterial strains, while they do not infect human cells.
Let’s delve into the perspectives offered by phage therapy with Novella Cesta, an infectious disease specialist at the Pisa University Hospital and among the founders of the startup Fagoterapia Lab.
A revival in search of new solutions
«Pharmaceutical pipelines are increasingly short of new antibiotic molecules, development is very long, and the costs to be borne are very high, while profits depend on the negotiated price. Moreover, antibiotic molecules quickly become resistant. Some doctors in the West have therefore wondered whether it might be possible to take phage therapy back into hand, using it as an alternative strategy», explains the expert about the revival that this approach has experienced over the last twenty years, a period marked by a rising wave of new publications on phage therapy, especially case reports and small series of cases based on the use of phages against different bacterial species.
The attention is focused, in particular, on bacteria considered priority by European authorities and the World Health Organization, in association or not with antibiotic therapy.
«Around 2010-2012, some clinical trials began on standard cocktails of active phages against one or more bacterial species, with good results at the 1 and 2 phases, but without reaching phase 3 and thus not leading to approval. This is because each phage is active against only one bacterium of a given species, for example only one type of Pseudomonas among all possible Pseudomonas. This greatly complicates things in terms of clinical trial design and a subsequent expansion of production – explains Cesta – Based on previous failures, new trials are now underway (also with new clinical study designs) by some companies that are trying to develop single phages or cocktails active against multiple bacterial species». It would, in this case, be products classified as biologic therapies, which could be used mainly for the most common and difficult-to-treat infections, such as pneumonia or prosthesis-related infections. The EMA (European Medicines Agency) is working on a specific guideline for the industrial production of such products under GMP (Good Manufacturing Practices), within the broader framework of European pharmaceutical regulations. Magistral phage preparations are excluded from this guideline.
Good knowledge and interest from physicians
Novella Cesta also explains the high level of knowledge about phage therapy among Italian doctors, as revealed by two surveys she conducted, the first together with Fagoterapia Lab, the second by SIMIT (Società Italiana di Malattie Infettive Tropicali), whose data will soon be published in a scientific article.
«The first survey showed that doctors, both specialists and general practitioners, were aware of the antibiotic resistance problem and the need for new solutions; more than 50% knew about phage therapy. The recent survey conducted by SIMIT among infectious disease specialists, across the country, indicated not only that 98% know about phage therapy, but that they would also be willing to use it. It isn’t a given; until not long ago people thought of it as something exotic, a reality confined in countries like Russia and surrounding areas. The growing awareness shows that today people are more willing to use alternative strategies, which does not mean less effective. It simply means looking more broadly at strategies not necessarily tied to the antibiotic molecule
This growing confidence in using phages to fight infections may also be linked to the early reports of cases treated in Italy, at least sporadically. «We are starting to use phage therapy: this increases knowledge and the possibilities to verify its effectiveness, to gain experience – emphasizes Cesta. – For the moment, the hospitals and medical teams that have tested this approach are about five, but I receive new requests every day».
A highly personalized therapy
In Italy, as in most European countries, phage therapy is not yet officially approved for clinical use and therefore remains experimental, accessible only through “compassionate use” procedures. At the moment, a physician must evaluate the specific case and prescribe the therapy for that patient by name, requesting authorization from the hospital’s ethics committee to treat them with a specific phage targeted at the exact bacterium causing the disease.
«There is currently no phage-based product approved for commercialization. When we have a patient with a chronic infection that cannot be treated with conventional medicine—for example because they have already undergone many interventions, or because they have a prosthesis and a particularly antibiotic-resistant bacterium—doctors ask us to help evaluate the patient’s condition, especially at the level of the implicated bacterium, and search for the most suitable phage», says Novella Cesta.
A second challenge is the production of phage preparations. As the expert notes, there are currently no certified production centers in Italy for these products, which are imported from abroad (especially Belgium and the United States).
«Phage therapy is also often administered in combination with an antibiotic: it is not seen as a replacement for use, but as a companion. Phages can enhance the activity of antibiotics where the antibiotics have not been effective. The combination therapy also reduces the risk of the bacterium developing resistance to both the phage and the antibiotic. Access to therapy is often requested for patients with cystic fibrosis who have colonizations or recurrences of Pseudomonas infections. We also have cases of osteomyelitis, infections of medical devices, recurrent urinary tract infections, recurrent pneumonias and bronchitis, and fragile patients. I think of patients who cannot be transplanted because of recurrent bacterial infections; the United States has substantial experience in these applications of phage therapy. To date, we can use phages for compassionate use in all infections, provided the condition of non-eradicability with standard-of-care is met. In the future, when phage therapy is regulated, it may be possible to access it even for infections that are not necessarily at the last stage of treatment, perhaps those that are difficult or may become complicated», the infectious disease specialist hopes.
Towards magistral preparations in Italy as well?
In addition to the aforementioned industrial productions of broad-spectrum phage cocktails, the second option for producing phage preparations tailored to the individual patient is to resort to magistral preparations by pharmacists, for example within hospital pharmacies. This is the approach chosen by countries that are leading the way at the European level—Belgium, France, and Portugal.
«This type of approach is not necessarily dependent on the EMA, although the Agency has defined its characteristics; each state can legislate in this sense at the level of its drug regulatory authority, with Italy’s AIFA (Agenzia Italiana del Farmaco) – explains Novella Cesta – To set up magistral production, the physician must prescribe a therapy based on an active pharmaceutical ingredient, in this case phages, which are then formulated by biologists and pharmacists. Structurally, this presupposes having a center equipped with appropriate laboratories that can produce according to recognized certifications and that are controlled.
In Belgium, for example, this task has been entrusted to the Military Hospital of Brussels in collaboration with Sciensano – the Belgian health institute (the counterpart of our Istituto Superiore di Sanità), responsible for carrying out all checks on the phages used.
«This type of setup certainly offers cost advantages over industrial productions; these are smaller-scale productions – emphasizes Novella Cesta – Another advantage is that access does not necessarily require compassionate use, which allows treating patients even where phage therapy might help improve the care path.»
From a regulatory standpoint, the setup of magistral preparations is based on the European Pharmacopoeia monograph on phage therapy products published by EDQM (European Directorate for the Quality of Medicines & HealthCare) in July 2024, and in Belgium on the one developed by the local Pharmacopoeia. The EDQM chapter could already be adopted by other member states; magistral therapy could become official across the Union. The national monographs to be adopted could take cues from the three countries that already have them, always following the EDQM General Chapter guidelines – the infectious disease expert hopes. There is no obstacle for a member state to query its regulatory authority based on these documents for a possible use. The channels in this sense have already started to form; it is a matter of making a stronger effort.
The effort has been taken up in Italy by SIMIT (Società Italiana di Malattie Infettive Tropicali) and SIM (Società Italiana di Microbiologia Clinica), which have also started a collaboration with SIFO (Società Italiana di Farmacia Ospedaliera) to raise awareness among pharmacists who could be involved in this kind of activity. “As a physician needing access to this therapy to treat my patients, I think we could look to other experiences, such as CAR-T therapies, to develop in Italy a network of specialist centers in strategic points across the country,” comments Novella Cesta. “It would be more convenient and less costly, with access for nearby areas. Focusing on using phage therapy where there is greater need to prevent resistance development or improve the care path, in my view the production could be sustainable in a short time. We’re working with AIFA, with the goal of starting from places where there are already people with experience and laboratories that could support this production. Given the experience in France and Belgium, it seems reasonable to create national reference centers: it’s a path that involves multiple specialists who could take on the most complex patients. It’s clear, then, that hospital facilities have budgets to respect, so we’ll also need to evaluate the economic impact».
Selecting the phage and the safety profile
As a precision medicine, phage therapy preparation always begins with identifying the exact strain of the target bacterium that struck the specific patient. Only on this basis can the corresponding phage be selected. «To treat as many strains as possible of the same bacterium, you need a wide biobank of phages from which to select the best one for the patient. In Italy there are currently no certified biobanks; at the University of Pisa we have our own collection of phages selected from the environment, from the strains circulating in the national territory» – says Cesta – «Biobanks larger than ours exist in the United States, Australia, Belgium and France. The largest and most important remains the one in Georgia, which has collected phages for more than a century. It is also possible to use several phages together to attack the same bacterium, an approach that has important biological advantages. Once ready, the phage preparation can be administered to the patient through all known routes of administration, depending on the site of infection. If a very deep site needs to be reached, for example, I can also use the intravenous route».
A point that distinguishes phage therapy from the use of antibiotics is the toxicity profile of this kind of preparation. Phages do not infect human cells, and even at the level of the intestinal microbiota they attack only their target bacteria. «That means greatly reduced risks related to alterations of the gut flora, such as Clostridioides difficile infection, as well as some adverse allergic events that may derive from sensitivity to a chemical active ingredient– explains the infectious disease specialist – Reading the case reports in the literature, adverse events appear to be almost nil, but to date no one has published a comprehensive review of all adverse events. There can be situations in which related events occur, for example fever after phage administration due to an immune reaction. Or secondary effects from bacterial lysis, which can release pyrogenic molecules. Even with inhaled administration, respiratory reactivity with inflammatory basis has sometimes been observed. In general, prolonged adverse events or liver or kidney toxicity have not been described. I am firmly convinced that phage therapy is far less toxic (in the true sense of the word toxicity, i.e., risk of toxicity even for the parenchyma) than a synthetic molecule», concludes Novella Cesta.
A bit of history
Bacteriophages were discovered in the 1915-1917 period by Frederick Twort and Félix d’Hérelle and quickly found wide use as antibacterial agents. In particular, phage therapy research took hold immediately in Georgia, where the scientist George Eliava founded in 1923 in Tbilisi the Institute of Phage Research that still bears his name today.
From there, phage research in Eastern Europe continued uninterrupted to the present day, especially among Georgia, Russia, and Poland. In the Soviet era, for example, phage therapy was widely administered to Red Army soldiers during World War II, as well as to populations of the former USSR.
The discovery of penicillin in 1928, however, led to a rapid decline in interest in phage therapy in the Western world, in favor of antibiotics and the emerging mass-production pharmaceutical industry. The industrial development of antibiotics from the 1940s onward contributed to the progressive decline of phage therapy in Western countries.
In Italy, the last phage preparation, the medicinal specialty Enterophagos, produced by the Laboratorio di chimica medica e dell’Antipiol, saw its manufacturing and marketing authorization revoked in April 1963.
Starting in the 2000s, the growing spread of antibiotic resistance has reignited international interest in phage therapy, fostering the development of clinical studies and research programs. Today phages are the subject of numerous research programs and clinical trials, with the aim of developing new therapeutic options against infections sustained by multidrug-resistant bacteria and difficult to treat with conventional antibiotics.
The process of selecting therapeutic phages
Bacteriophages can be divided into two broad macro-categories, depending on the type of replication cycle adopted and the consequent interaction with the host bacterial cell.
The phages used for therapeutic purposes are strictly lytic, meaning they infect the bacterium, replicate inside it, and cause the cell to burst as a result of membrane lysis. Temperate phages, on the other hand, integrate their genome into the bacterial genome and replicate with it, passing to subsequent generations of daughter cells. In doing so, they can give rise to virulence factors, toxins, or antibiotic resistance genes, making them unstable and much riskier for clinical use.
The selection of phages for therapy begins, first of all, with sequencing the genome and discarding temperate phages. The lysogenic phages thus obtained are subjected to a phagogram, a microbiological test that allows determining their ability to lyse the target bacterium.
Added to this are other laboratory tests to assess phage resistance to various pH and temperatures, as well as a characterization of the ease of replication in the desired quantities. The production of the chosen phage for therapy takes place inside selected bacterial cell-factories.
From the October 2026 issue of Karla Miller
Bibliography
- Naureen Z, Dautaj A, Anpilogov K, et al. Bacteriophages presence in nature and their role in the natural selection of bacterial populations. Acta Biomed. 2020;91(13-S):e2020024;
- Petrovic Fabijan A, Iredell J, Danis-Wlodarczyk K, Kebriaei R, Abedon ST. Translating phage therapy into the clinic: Recent accomplishments but continuing challenges. PLoS Biol. 2023;21(5):e3002119;
- Pirnay JP, Djebara S, Steurs G, et al. Personalized bacteriophage therapy outcomes for 100 consecutive cases: a multicentre, multinational, retrospective observational study. Nat Microbiol. 2024;9(6):1434-1453;
- Marongiu L, Burkard M, Lauer UM, Hoelzle LE, Venturelli S. Reassessment of Historical Clinical Trials Supports the Effectiveness of Phage Therapy. Clin Microbiol Rev. 2022;35(4):e0006222;
- Hitchcock NM, Devequi Gomes Nunes D, Shiach J, et al. Current Clinical Landscape and Global Potential of Bacteriophage Therapy. Viruses. 2023;15(4):1020;
- Liu D, Van Belleghem JD, de Vries CR, et al. The Safety and Toxicity of Phage Therapy: A Review of Animal and Clinical Studies. Viruses. 2021;13(7):1268;
- Marino A, Stracquadanio S, Cosentino F, et al. Phage to ESKAPE: Personalizing Therapy for MDR Infections-A Comprehensive Clinical Review. Pathogens. 2025;14(10):1011.
- Sippel K, Velimirov B. Phage Therapy: Application and Related Problems-A Review. Life (Basel). 2025 Dec 30;16(1):57;
- Blasco L, Bleriot I, Fernández-Grela P, Paño-Pardo JR, Oteo-Iglesias J, Tomás M. Pharmacokinetics and pharmacodynamics studies of phage therapy. Estudios farmacocinéticos y farmacodinámicos de la fagoterapia. Farm Hosp. 2025;49(6):407-412;
- Fuerst-Wilmes M, Respondek V, Schramm M, Lilienthal N, Buss K, Duechting A. Regulation of phage therapy medicinal products: developments, challenges, and opportunities. Front Cell Infect Microbiol. 2025;15:1631359;
- Moon K, Coxon C, Årdal C, et al. Considerations and perspectives on phage therapy from the transatlantic taskforce on antimicrobial resistance. Nat Commun. 2025;16(1):10883;
- European Medicines Agency, Draft guideline on quality aspects of phage therapy medicinal products, EMA/CHMP/BWP/1/2024, 16 aprile 2025; consultazione pubblica chiusa il 30/4/2026;
- Phage therapy medicinal products, European Pharmacopeia, Supplement 11.6, General Chapter 5.31, July 2024;
- Pirnay JP, Verbeken G, Ceyssens PJ, et al. The Magistral Phage. Viruses. 2018;10(2):64
Abbonati a Karla Miller
